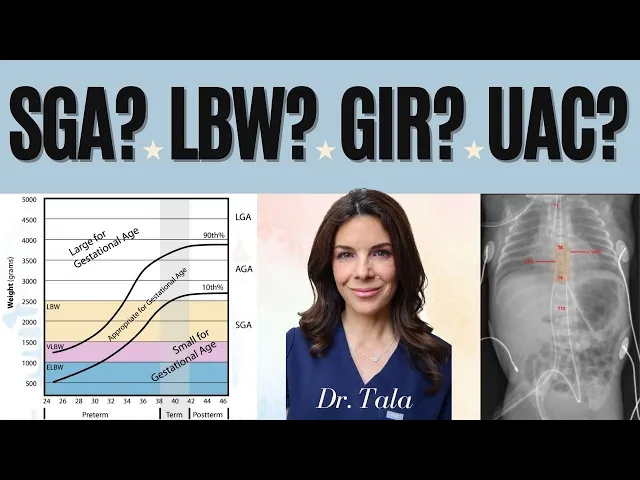
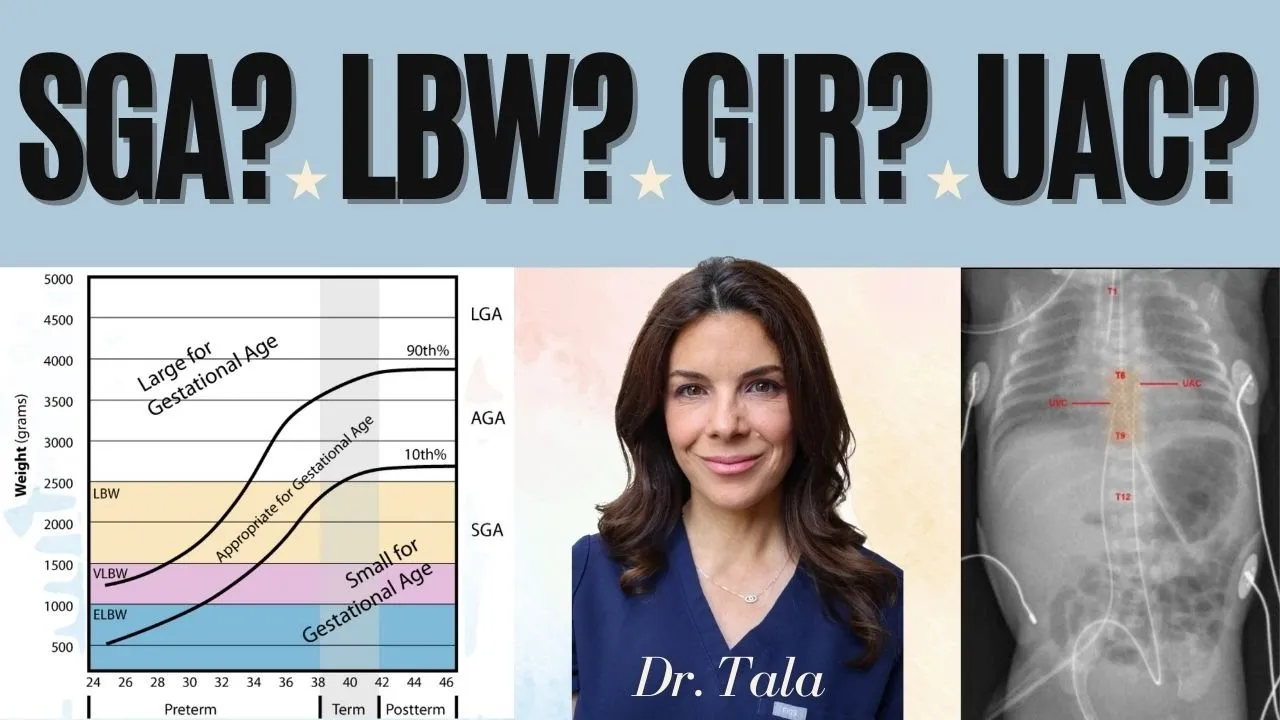
I'm sure that anybody new to the Nick who feels like there are so many equations and numbers that you have to learn I promise you that in a couple of years this is all going to feel like you've known it forever hi I'm Drtala and I've been a neologist for over 15 years so today in this video I'm going to go over all those definitions and numbers and equations that we use so freely in the ncu we'll start with General neonatal ones today as well as some more definitions and numbers that are involved with feeding and nutrition in the next video we'll go over kind of all the other systems respiratory and blood and everything else let's start with gestational age of a baby so any baby born below 37 weeks so 36 and 67 is considered pre-term if the baby is born at 37 weeks until 41 and 67th weeks so 37 weeks until 42 weeks then that baby is considered tone now we used to just call that entire period term and then as more and more studies came out recently we figured out that depending on where the babies were born within those kind of five weeks then that would also affect their prognosis so even those dates were uh broken down even more early term is 37 to 38 and 67 weeks these babies don't do as well as the full-time babies full-time babies are born 39 to 40 and 67th weeks and then the late term babies are born from 41 to 41 and 67 weeks if the babies are born after 42 weeks then they're considered postterm late term and postterm babies generally don't do as well as well as full-term babies and then the pre-term babies are also divided into groups and we also know that the younger the baby is born the smaller the gestational age of the baby generally the worse prognosis so late pre-term is between 34 and 36 and 67 again anything less than 37 weeks is considered pre-term the moderately pre-term a 29 weeks to 33 and 67 and the extremely pre-term a baby's born below 29 weeks so 28 and 67 so as an aside the whole neonatal Community is trying to come up with further subdivisions for those tiny babies but we haven't figured out the word yet now let's go over the classification based on their birth rate so if a baby is born born at less than 2,500 G the baby is considered low birth weight It Doesn't Matter What gestational age they're born at less than 2,500 gam is low birth weight if they're born at less than 1,500 G then they are considered very low birth weight and if they're born at less than 1,000 gram or 1 kilo then they're considered extremely low birth weight and that's kind of always upset me because there's like a kilo between the first two numbers and then only 500 G between the second two but still those are the definitions all babies can lose a little bit of weight in the first week to two weeks of their lives and in those first few days especially if the baby is in the NICU especially if they're tiny you want to calculate their percent weight loss from their birth weight a lot of computer programs do this naturally but if you've completely forgotten how to do percentages I'm going to go over an example let's say that you had a 27 weer born at 850 g and the baby is now 800 G so so so far the baby at like let's say day of life four has lost 50 g so you do 50 divided by the initial birth weight which is 850 times 100 and you get 6. 25 so this baby so far has lost 6. 25% of its birth weight preey babies can lose up to about 15% of their birth weight and can take a couple of weeks to get back to their birth weight ter babies generally lose up to about 10% of their birth weight and they should get back to their birth weight in a shorter period of time for many hospitals in the US if a baby is born below a certain gestational age or a certain weight they're automatically admitted to the ncu a lot of those hospitals use 35 weeks so if you're born at less than 35 weeks or less than 2 kilos somewhere between 18800 gr and 2 kilos you're automatically admitted to the niku about 75% of 34 weekers will need some sort of additional niku help about 50% of 35 weers and about 25% of 36 weers will need some sort of additional niku help beyond what like the nursery can offer so if you do have a late pre-term baby who's staying with a mother make sure that that baby is being carefully monitored with sugars and feeds and everything else what about the term SGA or small for gestational age it is exactly what it sounds like if the baby plotted on the growth curve is at less than the 10th percentile for that gestational age then the baby is considered sgaa so you have to know the baby's gestational age and you have to know the baby's birth weight and then you have to plot them on the weight curve for the gestational ages and see where that baby lies to actually make that diagnosis of sgaa LGA is similar it's large for gestational age so again you have to plot the baby out if the baby is above the 90th percentile then the baby is considered LGA so sgaa and LGA are dependent on the gestational age whereas if you're low birth weight then that's just objectively you're less than 2,500 gr another two phrases that we use a lot are the post-menstrual age and the corrected age so for example let's say that a baby was born at 28 weeks so that's the gestational age a baby was born at 28 weeks now let's say the baby is 14 days or 2 weeks old so the chronological age is 2 weeks so the postmenstrual age for that baby is 30 weeks 28 plus the 2 weeks corrected age is usually used more once a baby leaves the niku so let's say for example that a baby was born at 28 weeks so effectively the baby was born 3 months early or 12 weeks early so let's say when that baby is 4 months old the baby goes to the pediatrician so the baby is chronologically 4 months old but actively because the baby was born 3 months early the baby's corrected age is 1 month I'm just going to break here really quickly and ask you to comment below and let me know where in the world your niku is we're actively trying to fill a map out from all the viewers and all the niku in the world so just let us know now let's move on from General neony stuff to kind of more fluid GI nutritional stuff and let's start with some commonly used measuring values in the NICU which for whatever reason in the US are all just used completely interchangeably so you really do have to know all of these so the first thing is 1 kilo equals 2.
205 lb and we use those completely interchangeably in the niku a lot of the growth curves are all done in kilos so ultimately you definitely need to be using kilos at some point parents are always asking about weights in pounds and by the way there is 16 o in a pound and volume so 1 mil is basically the same as 1 cubic cm and one mL of milk or one cc of milk weighs about 1 gram then 1 o is about 30 MLS about 30 G maybe 28 to 30 gr a tablespoon is 15 MLS and a teaspoon is 5 MLS these are also commonly used by parents in the unit tablespoon and teaspoon and stuff when we admit babies to the unit the older and the larger they are generally the lower the amount of fluids that they need need so a term baby when they're admitted to the unit we might start them on 50 to 60 MLS per kilo per day whereas a tiny preey baby we may start on 100 to 120 MLS per kilo per day if a baby doesn't want to eat po by mouth then we would start feeds at somewhere between 20 to 30 MLS per kilo per day and we'd slowly increase the feeds if the baby's tolerating it and ultimately you're taking a baby whether they're pre-term or term up to about 140 to 16 60 MLS per kilo per day hopefully on the feeds we approximate that there are about 20 calories in every ounce or in every 30 MLS of breast milk as you all know from anybody that's ever worked in the niku the breast milk can look so different when the mother hands it to us so sometimes it looks like really watery and pale obviously that's probably going to be lower calories and sometimes it just looks like churned butter like it's thick whitish cream and that's probably going to have a lot more calories per ounce premature babies need a lot of protein and calcium and phosphorus and just other nutritional elements so they would have to take a lot of the breast milk to be able to get all of that so what we can do to the breast milk instead is actually add whether it's breast milk fortifier or or formula based fortifier to the breast milk to increase the calories and then also give some of the other nutrition that the baby need so we can add two calories or four calories or six calories or eight calories to make it 22 24 26 28 calories per ounce a growing baby needs somewhere between 100 and 130 calories per kilo per day so for example if a baby is on 160 MLS per kilo per day of 24 Cal formula or breast milk fortified with formula then basically the baby is getting 128 calories per kilo per day so 160 / 30 * by 24 is 128 calories per kilo per day so a perfect amount of calories for a growing baby every single day that a baby is in the unit we should be calculating or adding up the amount of volume as well as the calories that the baby is receiving and if it's just from feeds then that's pretty straightforward if the baby is on tpn as well as on feeds then obviously we have to calculate how much the tpn is giving the baby most tpn computer programs will do this for they'll calculate the number of calories and everything else directly but just for you to remember in one gram of carbohydrate there are four calories in 1 gram of protein there are four calories and in 1 gram of fat there are nine calories in the US we generally feed babies Q3 hours so every 3 hours we give them a feeding if the babies are younger we might do this uh less frequently so maybe Q4 maybe even q6 hours other places in the world may feed babies different ly maybe Q2 hours maybe even continuously which is why it's even more important that you actually calculate the total volume over the previous 24 hours what is the G or the glucose infusion rate basically it's the amount of carbohydrate that we're giving to a baby per minute and that g should be somewhere between 4 to 8 milligram per kilo per minute we don't really want it to go a lot below four because the brain especially needs sugar as a subst St for metabolism if a baby is not gaining weight or for example the mother had diabetes and it's an infant of a diabetic mother then the G may have to go up much much higher than eight so it really is important especially in these cases to calculate the G and this is the way I calculate the G so it is equal to the concentration of the sugar that you're giving in gram per 100 ml so for example if it's d10 then that's 10 gram of sugar in 100 MLS so the concentration of the sugar times the volume that you're actually giving to the baby in milliliters per kilo per 24 hours divided by 144 so let's say that you have a baby that you're giving 144 MLS per kilo per 24 hours and you're giving d10 to this baby so 10 * 144 / 144 is 10 so your G in this situation is 10 if you want more examples or to actually explain how we arrived at that formula then go look at the GI video we made what about urine output in a baby well as you all know in the first 24 hours babies only have to urinate once so we don't normally really count the actual urine output in the first 24 hours just present after that babies should be urinating between 1 and 5 MLS per kilo per hour so notice how ridiculously we talk about urine output every hour but we talk about the fluid volume in 24 hours because obviously the urine output can change a lot from hour to hour so let's do an example let's say that a 2 kilo baby in a 24-hour period urinates 132 MLS obviously the diapers are being weighed to calculate the 132 MLS or the baby has a catheter or whatever so the baby pees 132 MLS so in 24 4 hours baby peed 132 so in 1 hour baby peed about 5. 5 MLS 132 divid by 24 so the baby's 2 kilos so 5. 5 / 2 is 2.
75 millit per kilo per hour now let's talk briefly about the equipment that we actually use when we're feeding babies whether entally or parentally so something that we all use very very frequently in the unit is an orogastric or nasogastric tube and obviously these need to be inserted carefully there are many equations and formula that kind of determine how far you should insert the NG or OG tube but one of the ones that's used most commonly is the length of the tip of the nose to the earlobe to the space exactly halfway between the zyo and the umbilicus there are also tables that will kind of show you what the minimum length the tube needs to be inserted depending on the maturity of the baby so I think everybody at bedside gets used to this I very rarely put in NG or OG tubes we know that the gold standard to make sure that the NG or OG tube is in the right position or in the stomach is to get an x-ray but obviously we don't want to expose a baby to radiation every single time we insert an NG tube or every shift it could be moving or whatever and and so the technique that's pretty much become the most common way of checking it now is to check for acidity in the stomach so if you pull back some of the secretions obviously if the tube is in the stomach then it should have a low PH the pH should be below five ideally or 5. 5 if the pH is above five or 5. 5 then you can't be certain that you know where that tube is maybe it's gone too far it's gone into the intestine maybe it's still in the throat or worst case scenario maybe it's actually in the lungs so we generally check the pH of those tubes and what about umbilical catheters how do we determine how far in they should be placed and how should we make sure that they're in the right distance well up until now we pretty much check with x-rays to make sure that they're placed in exactly the right place and we'll talk about that in a second although we can also be tricked with x-rays I mean it's a 2d view basically so pretty soon probably the standard of care will be to check umbilical catheters with ultrasonography with bedside ultrasonography so how far should the catheters go in and what equations do we use so for a UAC and we've all established that the uac's should be high now so kind of like in the aor then the one that we use most commonly is three times the weight of the baby plus 9 so for example if the baby is 2 kilos then 3 * 2 is 6 + 9 is 15 and then I'll add maybe a centimeter or so for the stump of the umbilicus so the weight is in kilos and the length is in centimeters another equation that's commonly used for the UAC is the umbilicus to shoulder distance plus 2 cm obviously we pretty much prefer the weight one because we're definitely going to be getting a weight on the baby and actually measuring the baby's length any part of the baby's length is just one more thing that we'd have to do in that low stimulation golden hour period then what about the UVC so the UAC if you remember kind of dips down and then goes back up again whereas the UVC goes straight up so we're always putting the UVC a smaller length than the UAC so generally for the UVC we'll just divide the UAC by two and then plus one so for example if we uh put the UAC in 15 cm divided by 2 is 7.
5 cm plus 1 is 8.