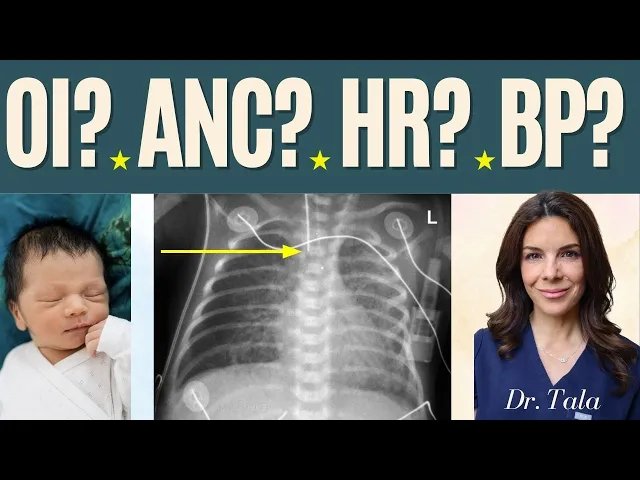
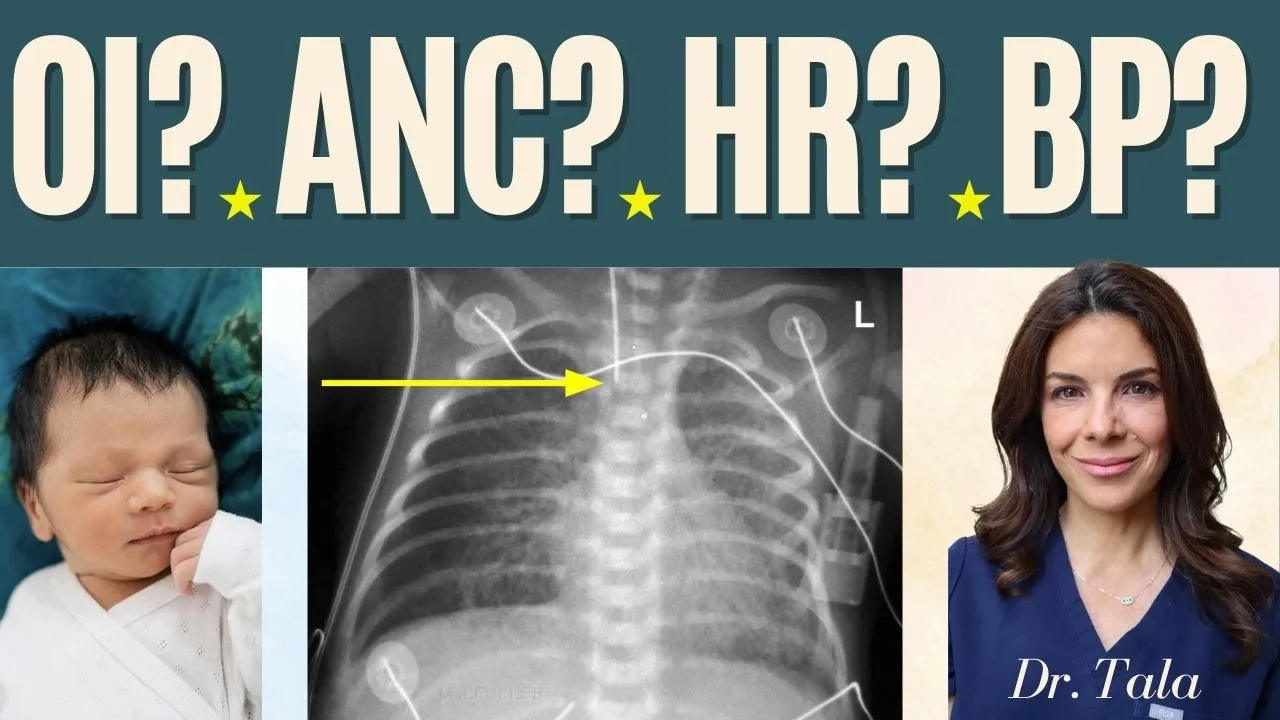
there are so many numbers and equations and formulas you're just expected to know when you're in the ncu hi I'm Drtler I've been a neonatologist for over 15 years we have already shot one video on General numbers and formula and stuff that you have to know for the niku and now we're going to go over kind of the rest of the stuff we'll cover vitals and respiratory stuff and blood stuff too let's start with the vitals that you pretty much should know for the ncu population and obviously we're talking temp blood pressure heart rate and respiratory rate so let's start with temp the most confusing thing about temperature in the US is that we use celsius and fahrenheit pretty much interchangeably like we'll even record them both on both babies and it gets super confusing I'm not even going to go over the equation of how to convert one to the other because it's ridiculous it involves subtracting 32 and multiplying by five nights and stuff you're never going to have to do that just plug it into an app it is confusing but there are four temperature numbers you have to know a fever is considered when a baby has more than 100° fah or more than 38° C so remember 138 and a baby is hypothermic just as scary or maybe even scarier if its temperature is less than 36. 5 de C or less than 97. 7 de F so remember those numbers 36 .
5 to 38 97. 7 to 100 what about blood pressure for neonates well the first thing you need to realize is that the smaller the baby and the younger the baby the lower the blood pressure is but the second thing you need to realize is nobody really knows what the ideal blood pressure is for the baby it's a very confusing subject we can't just say every preey baby is hypertensive so think about it logically though why do you have to have a good blood pressure you need a good blood pressure so that the heart is pumping enough blood and oxygen around the body so that all the cells in the body are receiving the oxygen and the nutrition that they need if the blood pressure is low then it means that the body probably isn't getting the nutrition and the oxygen it needs so we can look at other signs that there are low blood pressure effects in a baby so for example if the perfusion goes down if the cap refill goes up the baby's really pale if the baby starts peeing less if the baby stops tolerating its feeds then these are all signs that could be considered a low blood pressure the reason I brought all that up is in a way all those signs are important are just as important as the actual numbers of the blood pressure so remember a blood pressure normally is the systolic the high one the diastolic and then the mean so the mean blood pressure is the average of the systolic and the diastolic generally the body spends longer in the diastolic so the mean blood pressure is closer to the diastolic number and as a very vague rule if you need to learn anything about blood pressures consider that the gestational age should be about the mean blood pressure so for example if you have a 30 weer then you want your mean blood pressure to be at least 30 this is a reasonable starting point but honestly if you've got a 30 weer who's not peeing and is has really kind of threaded pulses and their mean blood pressure is 30 then that is hypertensive for that baby so in summary look at the numbers but also look at the baby when you're thinking about the blood pressure what is a wide pulse pressure and this is something that we see pretty often in babies for example with a PDA or even in kind of early sepsis and this is much easier to actually Define so a wide pulse pressure or a pulse pressure is considered to be wide if you double the diastolic and it that number is still less than the systolic so for example somebody tells you that some baby's blood pressure is 60 systolic 20 diastolic is that wide I know you're all kind of thinking it feels wide so let's actually do the maths so the diastolic is 20 multiply it by 2 is 40 40 is still a lot less than 60 so yes 60 over 20 is a wide pulse pressure a normal respiratory rate for a newborn is somewhere between 40 to 60 breaths a minute immediately after a baby is born they may be breathing a lot faster than this as they're trying to get the fluid out of their lungs and a newborn's heart rate is somewhere between 100 to 180 beats per minute the younger the smaller the baby is generally the faster the heart rate is older babies especially if they're fast asleep can have low resting heart rates in the 80s or '90s what's a lot more important about the heart rate and really all of the vitals is where the vitals of that patient have been so make sure that you get the Baseline vitals on your patient so that you know if they go up or down there's been a difference what about the ideal oxygen saturation for a baby or kind of the fifth Vital sign so if a baby is on room air then obviously we want the baby SATs to kind of be in the '90s it's okay if the baby goes up to 100% but if we're actively giving the baby oxygen we do not want the baby SATs to be 100% And the reason is is we know that when we give babies really high oxygen exogenously and their saturations are like constantly 99 100% those babies have a higher risk of getting Roop so bad retinal eye disease as well as worse BPD so worse chronic lung disease so we don't want babies to have a really high saturation ideally we probably want a growing baby saturations to be in the low 90s so generally our alarm limits are somewhere between 88 and 95% like everything in medicine there are so many exceptions if you have a baby with bad pulmonary hypertension you probably want the SATs higher than 88% and while we're talking about saturations how do we Define an apnea an apnea is when a baby stops breathing for 20 seconds or it's less than 20 seconds if that apnic event is associated with a color change a desaturation or braady cardia so that is what would be considered an actual apnic event I'm going to say something very basic now just to make a 100% sure that everybody knows this the amount of oxygen that we breathe in room air is 21% so if a baby's on a breathing machine or on a nasal canul on CPAP the lowest amount of oxygen that you're ever going to give that baby and none of the machines can actually really give lower than this well is 21% the maximum oxygen that a b baby can be on is 100% so if a baby is already on 100% F2 and the baby's sats are in the 60s you can't go up any higher on the F2 I know you know this I'm just making 100% sure that every single person watching this knows it now let's talk about some delivery room numbers when you are in the delivery room and you're setting up the F2 for a delivery then right now the NRP recommends that for a turn baby you set up the F2 at 21% so if a full-time baby is coming out you're just giving that baby room air and if it's a preey baby then set up the fi2 somewhere between 21 and 30% and also according to NRP two more numbers that you need to know at what point do you actually give positive pressure ventilation well if the heart rate is less than 100 then at that point you should start giving the baby breaths positive pressure ventilation or obviously if the baby's not breathing breathing and when you start chest compressions well you start chest compressions after the positive pressure ventilation is clearly not working and hopefully you've already got an endot trical tube in and the heart rate is staying below 60 so if the heart rate is below 60 despite good ppv then you should start chest compression so remember those two numbers 100 and 60 what about if you're in the delivery room and you actually have to intubate the baby what size tube should you use how far should you push it in what blade should you use let's start with the actual ET tubes the endot tral tubes in the niku we are using endot tral tubes between 2. 0 and 4.
0 but honestly the vast majority of them between 2. 5 and 3. 5 a good way to remember roughly what size ET tube a baby needs is 1 2 three when a baby is between 1 and 2 kilos the baby needs a 3.
0 ET tube if the baby's above 2 kilos then the baby pretty much needs a 3. 5 if the baby's below 1 kilo then the baby pretty much needs a 2. 5 then the tiny tiny ones maybe the 22 23 weekers that you literally can't fit a 2.
5 in you'll use a 2. 0 and the really big babies the turn babies that you don't want any leak whether it's a bad CDH or it's a big surgical babies then those are the ones that you'd use a 4. 0 on another good pneumonic for this is at 25 weeks use 2.
5 at 30 weeks use 3. 0 at 35 weeks use 3. 5 I mean they're both pretty similar but honestly the truth is you never really know the size of the baby's vocal cords unless you're actually going into intubate and what about the size of the actual blades the lingos Scopes so most of the time with niku babies we're using a size zero blade for the really big babies then you might need a size one and for the little babies kind of less than kind of 28 weeks you'd use a double zero for the really tiny ones there's now a triple zero available these are used very rarely and then how far do you actually push in the endot tral tube well the formula that we've always used is the weight of the baby plus 6 cm so for example if you intubate a 2 kilo baby then it should be 2 + 6 so you should push the endot tral tube in 8 cm but as a quick aside we've also figured out that the really small babies the ones that are kind of considerably less than a kilo generally need the tubes in somewhere between 5.
5 and 6 cm so that equation doesn't really work for the tiny little babies like a 22 23 weer it pretty much has that endot tral tube in somewhere between five and 5. 5 CM but whenever you do intubate a baby you should be checking its position with a chest X-ray and ideally you want the end of the endot tral tube to be between the clavicles and the Corina and the Corina is where the tracha splits off into the bronchi so kind of midway between that is a great position for the endot tracheal tube there are a couple more respiratory numbers that I want to go over and the first one is the oxygen saturation in the delivery room realize that it takes several minutes for a baby to actually pink up and at one minute of Life a baby saturations are expected to be about 60% so look at this table from NRP we really don't expect the baby to have an oxygen saturation above 90% until they're about 10 minutes old so we constantly have to remind ourselves of this so we don't get overly excited that the SATs at 5 minutes is still in the 80s and everybody wants to give oxygen and stuff it takes time for a baby to pink up the other respiratory equation that we use is something called the oxygenation index so basically this is a marker of how bad the lung disease or how poorly this baby is actually oxygenating and the way that we calculate it is the mean airway pressure that the baby is on multiplied by the F2 divided by the pao2 so divided by the oxygen that's dissolved in the baby's blood not the oxygen saturation so you can only get the pa2 by actually doing an art stick and looking at the number on the blood gas result so as an example let's say you're on the oscillator and your mean is 20 on the oscillator the mean is very obvious the other machines will still calculate it but it's kind of easiest on the oscillator the mean is 20 and you're on an F2 of 100% honestly the only times I ever calculate the oi is when the baby's on 100% so the mean of 20 times 100 and let's say that the baby's pao2 is 42 so 20 * 100 / 42 = 47 that's a really high I oi once your oi is above about 40 then if the baby's a candidate you're thinking about ECMO if the oi is above about 20 to 25 then you should be considering IO okay if you've reached this far then can you like this video and then tell us where in the world you're actually watching this from we are filling in a map of the world from where every where every NICU is so we would love to be able to finish that map now let's move on to some hematological or blood numbers and equations that would be very helpful to know these are all a little bit different from actual adult numbers so I think it's very important that everybody kind of understands that so the first thing is you should realize that a normal WBC count for a neonate is somewhere between five and 30,000 so kind of lower as well as higher than an older kid or an adult and there are two numbers that we like to calculate or two equations that we like to use in the ncu and those are the I over T Ratio or the immature over total ratio as well as the absolute nutrifil count before you calculate either of them you have to know all the cells in the myogenous lineage actually in the nutrifil lineage and as you all know the neutrophils are the type of the white blood cells that take up about 40 to 60% of all the white blood cells and they're very active in fighting infections the bone marrow makes immature neutrophils and then they slowly develop until until the nutrifil are mature in a healthy person the bone marrow would wait until the nutrifil are mature before it spits them out into the blood circulation but if a patient is ill and is desperate to get anything out there to fight infections then sometimes the bone marrow will spit out some of those immature forms if the bone marrow is really sick then it's basically barely spinning out any wbcs let alone any neutrophils and this could be a really bad sign for a baby having an infection or neck or something so one of the ways that we can calculate this is the absolute neutr count so really out of all the wbc's you want to know how many of them are actually from the nutrifil lineage so you look at your WBC count and then you look at the percentages of all the neutr precursors as well as the neuts add them up and then multiply them by the number of wbcs that you have obviously you need to know all the precursors of the neutrophils to be able to count them out so the precursors are a myoblast that's the earliest prosite myosite metam myosite band and then a segmented nutrifil so let's say our total WBC count is 12. 4 th000 and we have 50% segmented neutrophils or segs 7% bands and 3% metamyelocytes and none of the others sometimes we only have bands sometimes we only have segs and we don't have any immature cells but in this case we have 50 segs plus seven bands plus three metamyelocytes so Al together we have 60% of the blood cells from the neutrophil lineage so the ANC here is 60% time 124,000 which is 7.
44 th000 we worry about sepsis or we worry about the baby's immune function when thec is less than 1,500 and if you want more details with this then go back and look at the WC lecture we made very early on in this Channel and what about the I over T Ratio or the imature over total cells ratio again this is all in the neutrophil lineage so again you have to realize which of those cells are immature so let's do another example let's say you have 3% promos 3% metam Milos and 5% bands and we have 15% segs so let's add up the immature cells that's 3 + 3 + 5 = 11 and then you have to do the ratio of immature over total so the which is immature plus SE so you do 11 divided by 11 + 15 so this equals 11 divided by 26 equal 42 so here your I overt ratio is42 a lot of people argue that any I of a t ratio above about.